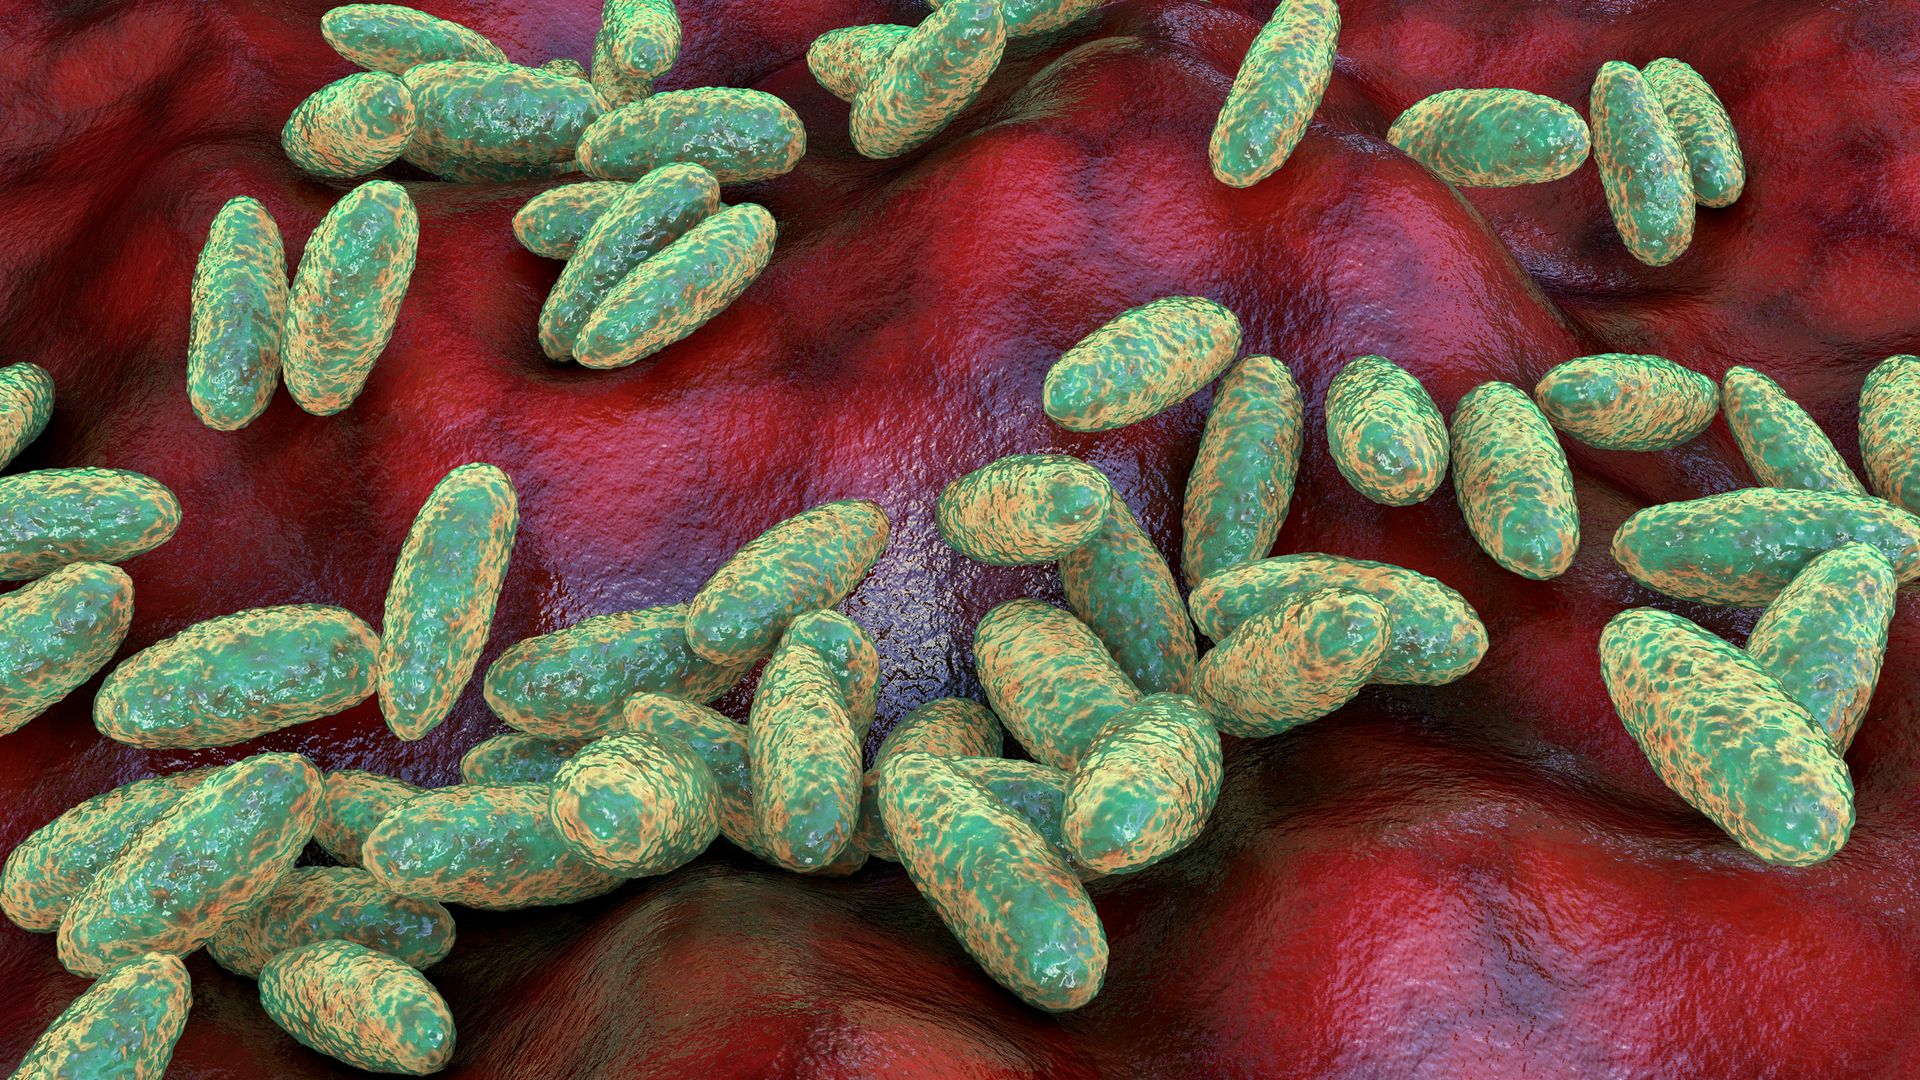
Infectious disease surveillance relies on early anomaly detection, particularly when dealing with high-consequence pathogens that exhibit rapid clinical progression. When a suspected case of pneumonic plague emerges, public health systems must immediately transition from routine epidemiological monitoring to aggressive containment. Understanding the threat requires deconstructing the transmission dynamics, the critical windows for medical intervention, and the structural protocols that govern outbreak control.
The Pathophysiological Baseline
Yersinia pestis operates through distinct clinical manifestations, determined entirely by the vector of exposure and entry site. Bubonic plague follows flea-borne transmission, localizing primarily in the lymphatic system. Septicemic plague involves direct systemic dissemination within the bloodstream. Pneumonic plague, however, represents the most critical operational threat due to its primary respiratory transmission capability.
The incubation period for primary pneumonic plague is exceptionally short, typically ranging from one to three days. Once clinical symptoms manifest, the pathophysiological cascade moves with extreme rapidity. The bacterium induces severe primary atypical pneumonia, characterized by hemorrhagic necrosis of the lung tissue, acute respiratory distress, and rapid circulatory collapse. Without immediate antimicrobial therapy administered within the first twenty-four hours of symptom onset, case fatality rates approach one hundred percent.
Transmission Vectors and Containment Mechanics
The epidemiological risk profile of pneumonic plague is defined by its ability to spread via infectious respiratory droplets expelled during coughing. This airborne vector bypasses the necessity of intermediate insect vectors, creating the potential for person-to-person transmission within enclosed environments.
Containment protocols dictate a multi-layered barrier strategy:
- Airborne Isolation: Suspected and confirmed cases require immediate placement in negative-pressure isolation rooms to prevent droplet dispersion within healthcare facilities.
- Personal Protective Equipment: Medical personnel must utilize high-efficiency particulate respirators alongside standard droplet precautions to mitigate occupational exposure.
- Contact Tracing and Prophylaxis: Epidemiologists trace all individuals who shared breathing space with the index patient during the infectious window. Post-exposure prophylaxis, typically involving oral or intravenous administration of specific broad-spectrum antibiotics, must be initiated immediately for all identified close contacts.
The Diagnostic Bottleneck
Rapid identification remains the primary structural vulnerability in plague management. Early clinical signs—fever, headache, weakness, and rapidly developing pneumonia with hemoptysis—frequently mimic standard community-acquired respiratory infections.
Diagnostic verification depends on a combination of rapid multiplex polymerase chain reaction assays, direct fluorescent antibody staining, and microbiological culture of respiratory secretions or blood. In the initial hours of presentation, before laboratory confirmation is secured, clinicians are forced to operate under a precautionary principle, initiating empirical antibiotic regimens based purely on epidemiological linkage and clinical suspicion. Delaying therapy until confirmatory testing is finalized significantly reduces survival probability.
Systemic Response Architecture
When a potential pneumonic plague event is flagged, regional and national health agencies execute a standardized escalation framework. This involves notifying international health authorities under the International Health Regulations, mobilizing specialized deployment teams for epidemiological field investigations, and securing pharmaceutical stockpiles to ensure uninterrupted access to effective therapeutic agents such as aminoglycosides or fluoroquinolones.
The efficacy of the response is measured by the velocity of the containment ring. Every hour shaved off the detection-to-treatment timeline exponentially reduces the probability of secondary transmission chains establishing themselves within the broader population.